
























 1
Consultation and scan review
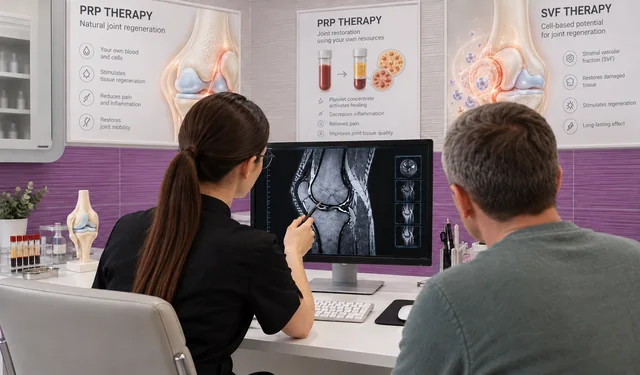
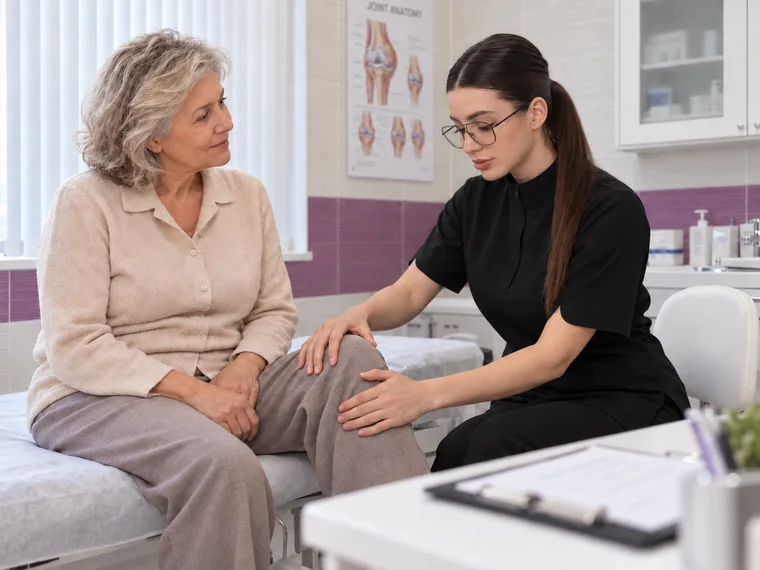
Before anything else, the doctor examines the joint and goes through your X-rays, MRI or ultrasound to see if the procedure is suitable. Scans can be sent to us ahead of time.
Cell therapy (SVF) and PRP for the knee, hip, shoulder and other joints. A free review of your scans before any decision
Consultation and review of your scansFree
Message us on WhatsAppFree online consultation · Reply within 15 minutes
Message our coordinator
Free online consultation · Reply within 15 minutes
Message us on TelegramMessage us on WhatsAppBy messaging us, you agree to our Privacy Policy
What it is
Everything used in regenerative joint treatment comes from you: platelet-rich plasma (PRP) is made from your blood, and the stromal vascular fraction (SVF) from a little adipose tissue. The doctor injects it into the painful joint to lessen inflammation and pain and to support the joint's inner tissues.
For someone with joint pain who wants to avoid surgery or delay it, or who has been told replacement is the only choice, this is worth considering. The doctor reviews your scans to assess the stage — earlier stages give a better chance of a lasting result.
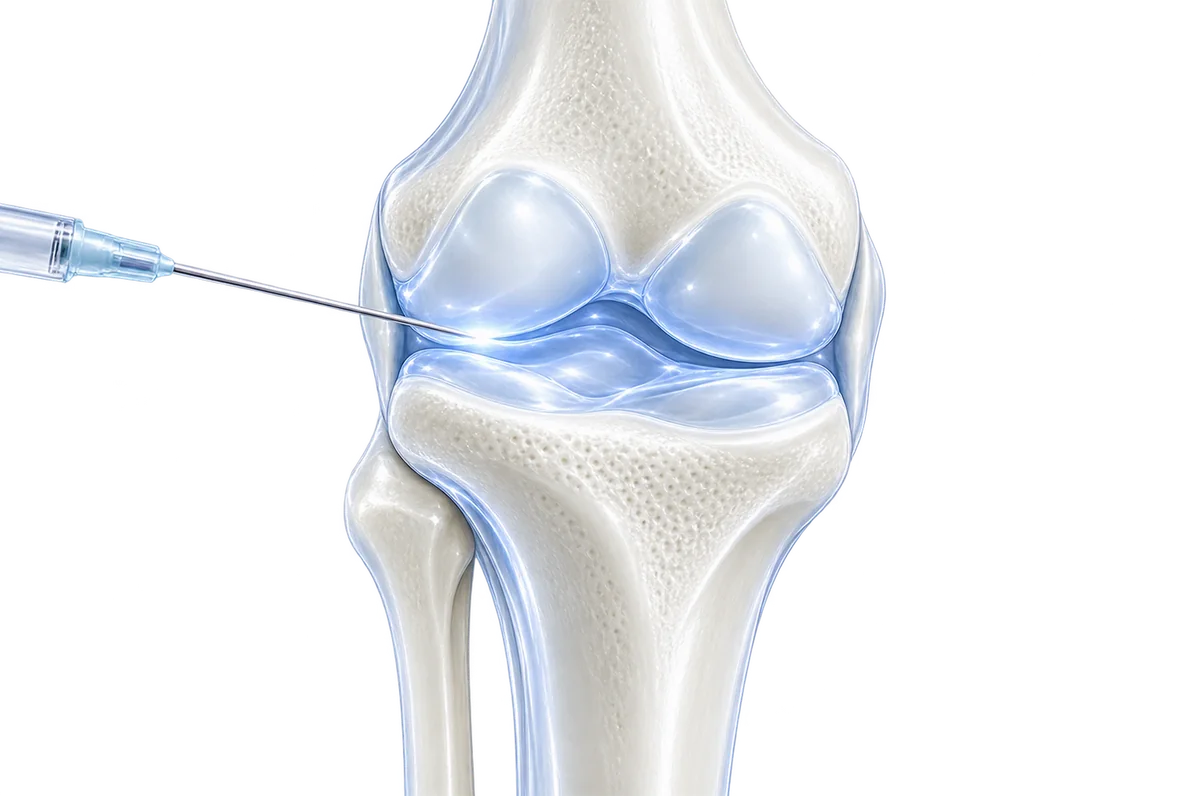
Examination and scan review come first; then the doctor decides whether the treatment suits you

Not sure the treatment is right for you?
Leave your number — the coordinator will ask for your scans (X-ray, MRI or ultrasound), and the doctor will tell you whether treatment without surgery suits you.
Find out if it suits meWhat we treat
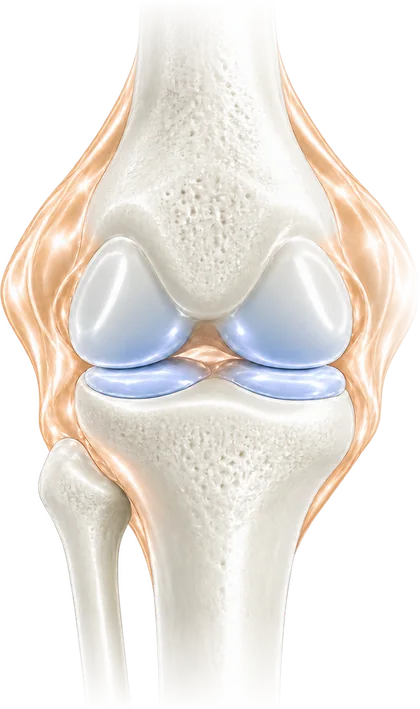 Arthritis
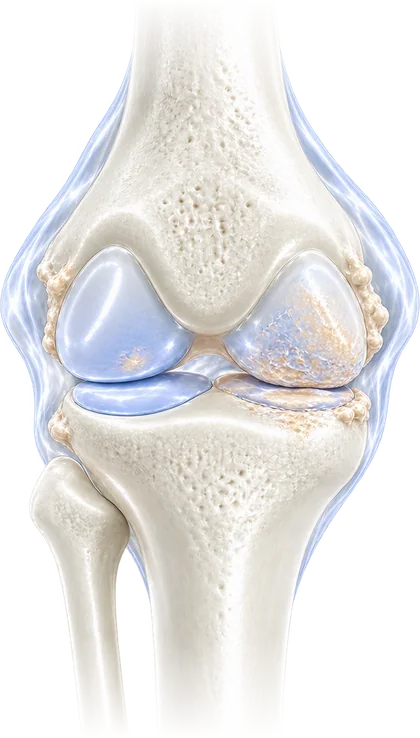 Arthrosis
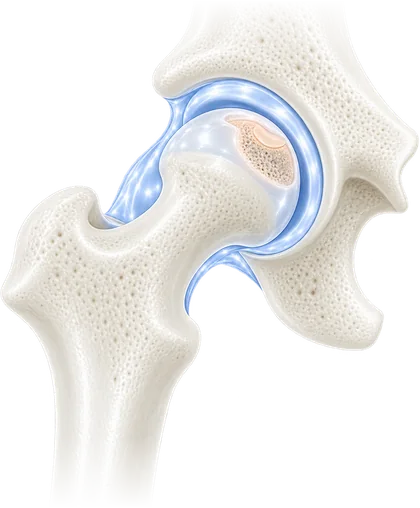 Avascular necrosis
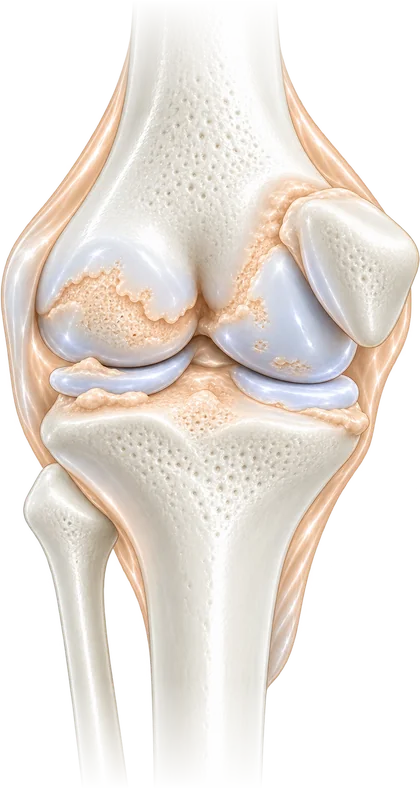 Osteoarthritis
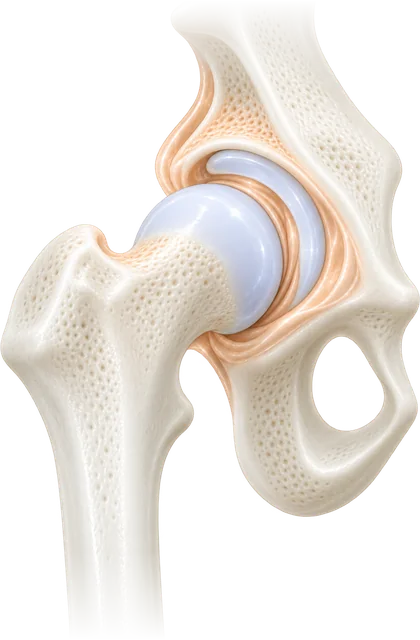 Coxarthrosis (hip osteoarthritis)
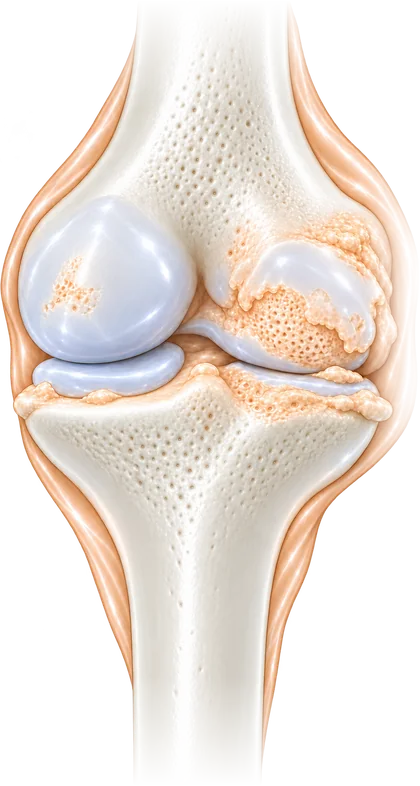 Gonarthrosis (knee osteoarthritis)
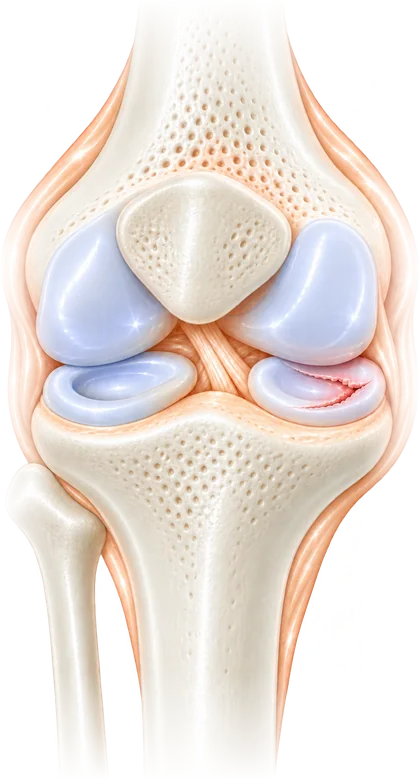 Meniscus pathology and injury
 Rehabilitation after injuries and surgery
 Inflammatory joint conditions
How it works
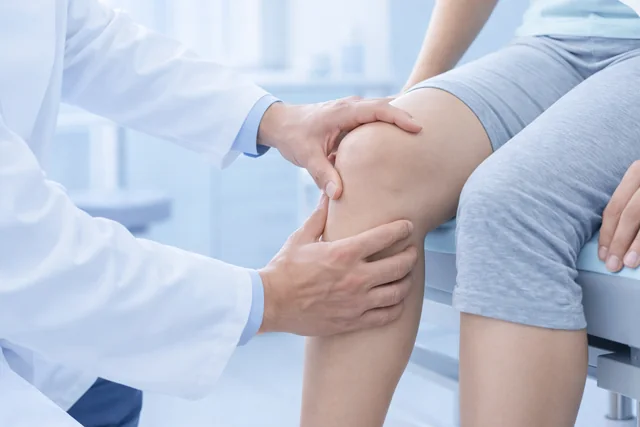
1Before anything else, the doctor examines the joint and goes through your X-rays, MRI or ultrasound to see if the procedure is suitable. Scans can be sent to us ahead of time.
 2
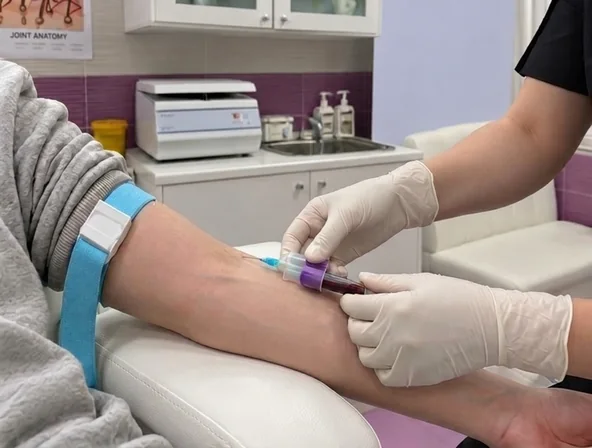
We take a small blood sample from a vein. From it, platelet-rich plasma containing growth factors is prepared later on.
 3
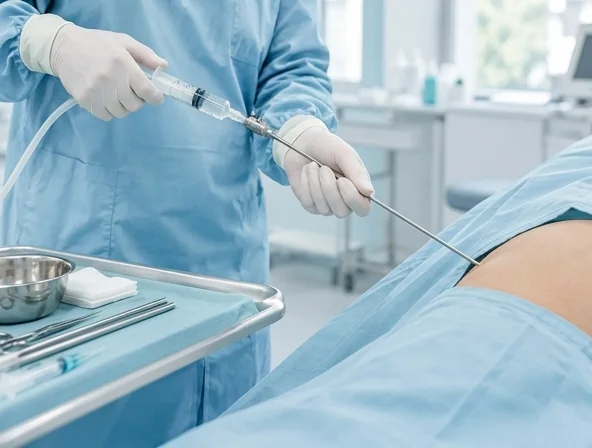
With local anaesthetic, a small amount of adipose tissue (around 30 ml) is taken via a puncture on the abdomen or inner thigh — without stitches.
 4
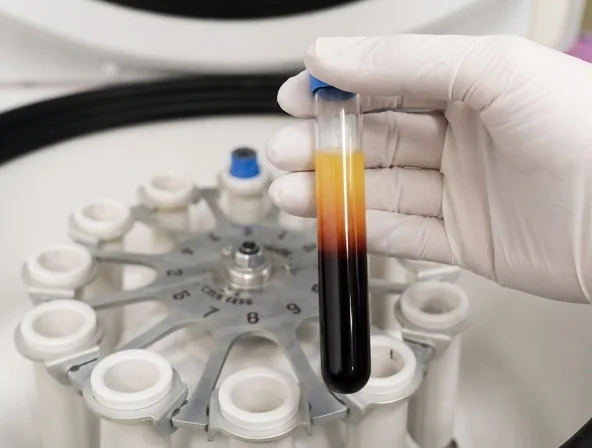
The centrifuge separates the sample into layers, the stromal vascular fraction is isolated, and it is then mixed with platelet-rich plasma.
 5
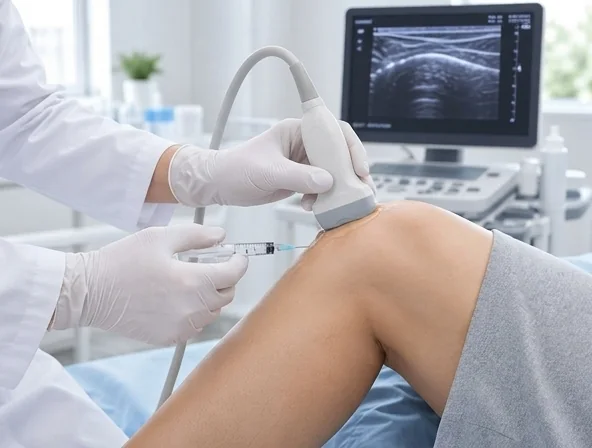
Directly into the affected joint: the prepared material is injected under ultrasound guidance for precise placement.
 6
No crutches, no hospital stay — and after the procedure the doctor keeps in touch to follow the joint's response.
Call or message us — our coordinator will contact you shortly and book your consultation

Results

The joint may ache a little more — this is an expected reaction.
The pain usually eases.

Mobility and activity improve.

The full effect develops.
How long it lasts differs from person to person and depends on the stage of the condition, body weight, activity and other factors — no one can promise a fixed result.
Comparison
Just your blood and your adipose tissue; donor and synthetic materials are not used
Processing a small sample of adipose tissue yields the stromal vascular fraction (SVF), a blend of cells that help tissue repair. The doctor combines it with your plasma and injects it into the problem joint.
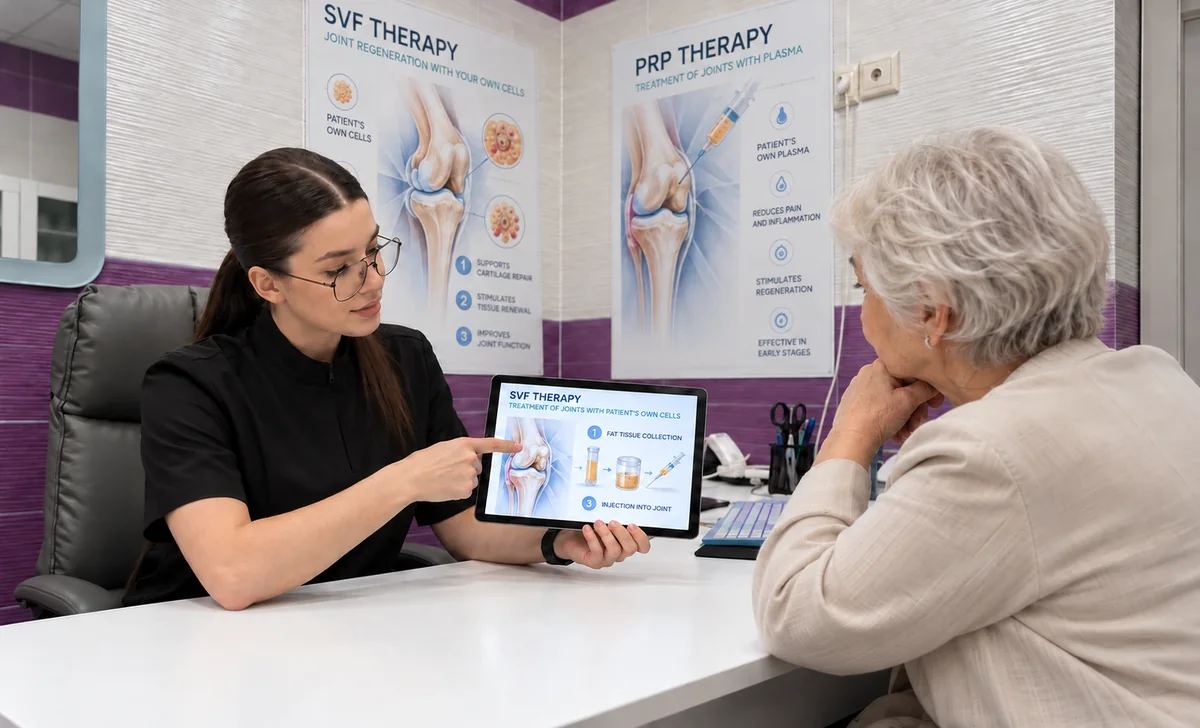
It tends to be used when the joint is more visibly changed and a longer-lasting effect is being sought.
The doctor separates plasma rich in platelets and growth factors from a small amount of your blood and injects it into the joint. This helps to calm inflammation and supports tissue repair.
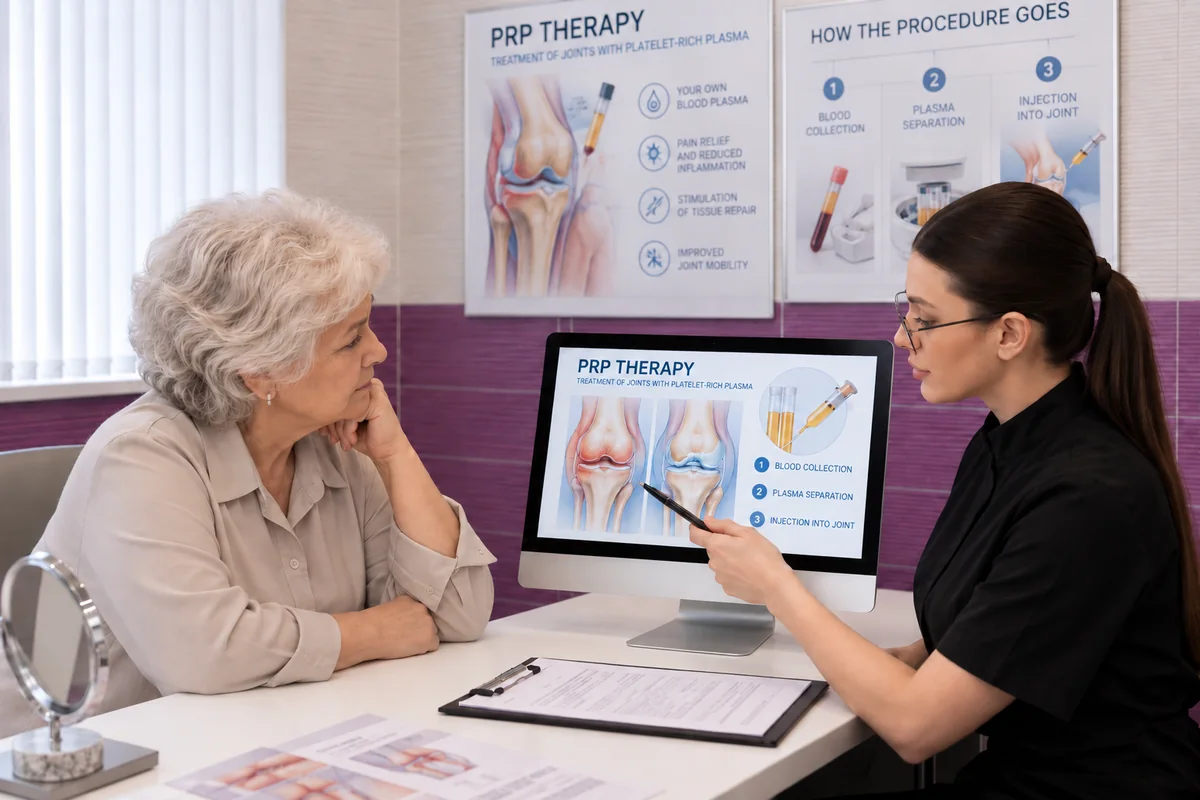
Used by itself as an injection course, or together with SVF.
The benefits and timings shown are averaged and given for guidance: the plan and recovery depend on your joint and individual features, and the doctor confirms them at the consultation.
At the consultation the doctor will review your scans and suggest a treatment plan
Free consultation
Joints
Small joints and large ones alike — your scans guide the doctor's choice of joint, method and number of injections
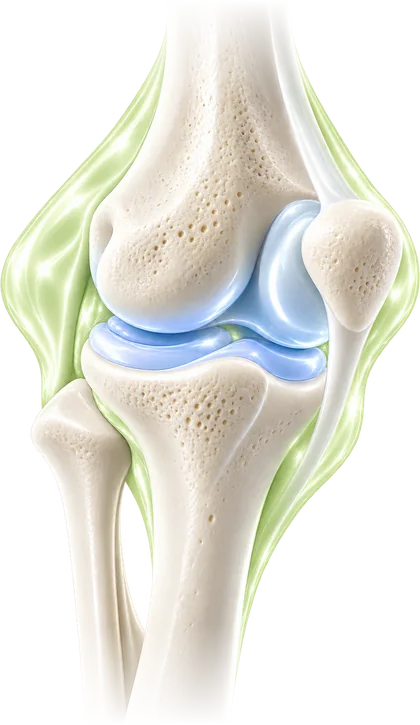 KneeWorn cartilage and meniscus issues, with pain on stairs and after walking
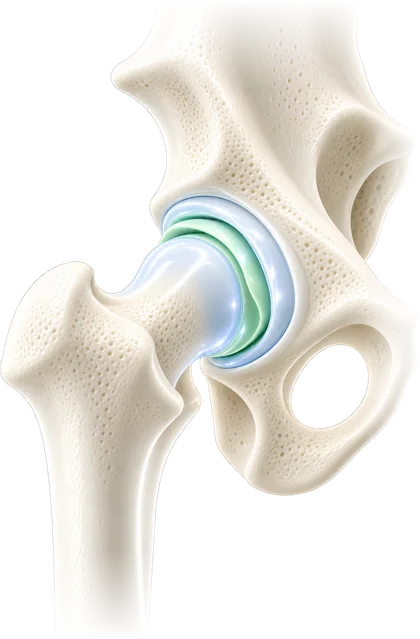 HipEarly hip osteoarthritis, groin pain, limited rotation
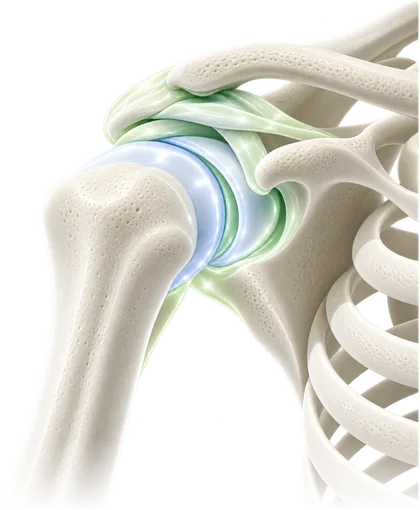 ShoulderPain when you raise your arm, worn joint and surrounding tendons
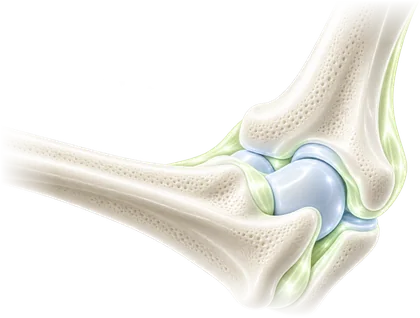 ElbowAching after strain from sport or overuse, joint surface wear
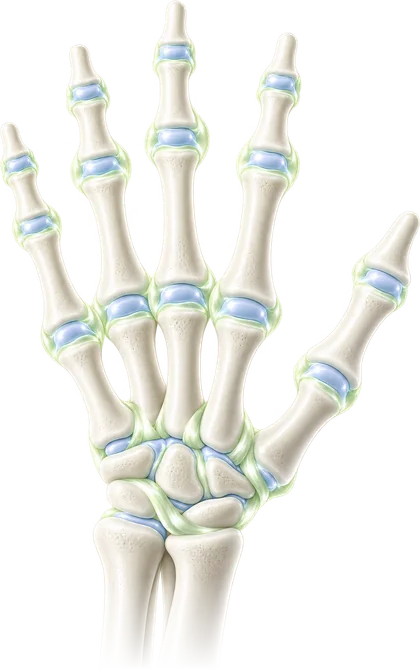 Hand and wrist jointsPain and stiffness in the small joints of the wrist and fingers
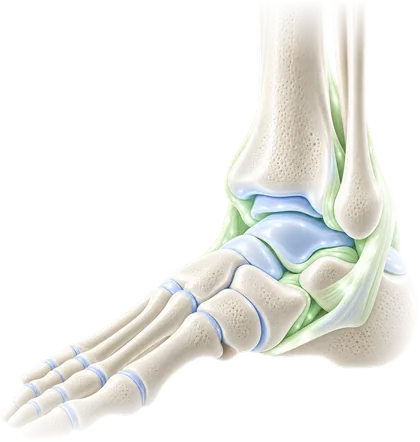 AnklePain and stiffness after sprains and old injuries
Advantages
Treatment without surgery: we work to save your own joint rather than replace it

Just your blood and your adipose tissue; donor and synthetic materials are not used
Small punctures in place of incisions, local anaesthetic, no long recovery programme
Send us your X-rays, MRI or reports and a doctor will assess them independently, free of charge
We stay in touch after the procedure and follow the result, not just the day of the injection
About the clinic
Modern equipment, comfortable rooms and care for every patient

We will answer your questions and find a convenient time for a consultation
By messaging us, you agree to our Privacy Policy
Request a free callPrice
Cost varies with the joint, the stage of the condition and the method; the doctor names it after the consultation
Free
Book — Consultation and review of your scansPrice at consultation
Book — PRP therapy (platelet-rich plasma)Price at consultation
Book — Cell therapy (SVF + PRP), one jointFAQ
Often, yes. For meniscus damage and knee osteoarthritis, PRP and SVF injections are used to ease pain and support the joint. The doctor reviews your MRI first and says whether this suits you.
One is plasma, one is cells: PRP is platelet-rich plasma from your blood, SVF a cell fraction from a small adipose tissue sample. As they act in different ways, doctors often combine them to boost the regenerative effect in the joint.
Both methods use your own tissue, so the risk of rejection or an allergic reaction is very low. As with any injection, temporary pain, swelling or bruising are possible, and infection is rare. The doctor explains the risks for your case at the consultation.
It varies between patients. After PRP the effect commonly lasts from several months to about a year, and after SVF possibly longer. Because duration depends on the stage of the condition and your body, nobody can promise a fixed result.
The procedure is not performed in people with cancer, acute infections or blood clotting disorders, in pregnancy, or during a flare-up of a serious chronic illness. The doctor checks for this at the consultation.
At early stages, PRP or SVF injections combined with exercise therapy and physiotherapy can reduce pain and improve movement. If the joint is already badly damaged, replacement may be the more realistic option — the doctor will tell you honestly after seeing your scans.
Early on (stages 1–2), the doctor may consider SVF therapy to support the femoral head's blood supply and delay joint replacement. In later stages surgery is generally required.
Joint replacement is a major operation: rehabilitation takes long, infection is among the risks, and an implant may one day have to be redone. With early or moderate changes it is often sensible to try keeping your own joint first.
Yes. Send your X-rays, MRI, CT or medical reports, and a doctor will review them free of charge and tell you whether the procedure could suit you and what else may be needed.
Usually in a day or two. There are no crutches and no long rehabilitation; for the first weeks the doctor gives recommendations on load and exercise.
Shoulder joint and rotator cuff problems are treated with PRP; in more advanced shoulder arthritis, SVF may be an option. The doctor first finds the cause of the pain, and that decides whether it suits you.
About the conditions
Arthritis is an inflammatory disease of the joints. Typical signs are pain at rest and at night, morning stiffness lasting more than 30 minutes, swelling, redness and warmth over the joint. Causes include autoimmune conditions such as rheumatoid arthritis, infections, gout and psoriasis.
It is gradual wear of the cartilage that covers the ends of the bones in a joint. When the cartilage thins, the joint loses its cushioning, the bones rub against each other, and pain, stiffness and crunching appear. It is a degenerative condition, not an inflammatory one.
Osteoarthritis is wear of the cartilage: aching pain on movement, crunching, stiffness after rest. Arthritis is inflammation: pain at rest and at night, swelling, redness and warmth over the joint. The approach to treatment differs, so the diagnosis comes first.
The method relies on your own tissue only, so there is no donor or synthetic material. Plasma is prepared from a small blood sample, and SVF from about 30 ml of adipose tissue taken through a puncture. This is how non-surgical joint treatment works for everyone in Nottingham.
Keeping a healthy weight and regular, joint-friendly exercise help the result last longer. The doctor explains which activities suit your joint and which loads to avoid — the same advice applies to every patient in Nottingham.
The price depends on how many joints are treated and which method is chosen. For patients from Nottingham, the doctor explains the plan and the cost at the consultation, which is free.
Nottingham sits on low hills along the lower valley of the River Trent, with Sherwood Forest to the north. It is not a mountain town, but a city built on gentle slopes still means regular gradients on the way to a bus stop, a tram or a shop. For a knee with worn cartilage or a hip with early osteoarthritis, a slope is often where the trouble first shows: pain climbing, a stiff first step after sitting, or aching after a long walk.
These are the same signs the medical team looks for when it reviews a case. The treatment described here uses PRP (platelet-rich plasma from your own blood) and cell therapy (SVF from a small sample of your own adipose tissue), both injected into the joint under ultrasound guidance. The idea is to ease pain and inflammation and to support the tissues inside the joint, with no surgery and no crutches afterwards.
The doctor decides whether this suits you only after an examination and a review of your X-ray, MRI or ultrasound. Chances of a lasting effect are higher at earlier stages, so describing honestly when the pain began and what makes it worse is a useful first step for the online consultation.
Met Office figures for Watnall, the station used for the Nottingham climate averages, show an annual mean temperature of 10.1 °C. January is the coldest month, with a mean maximum of 6.9 °C and a mean minimum of 1.7 °C, and there are on average 36.9 days of air frost a year. Rainfall totals 715.6 mm over 125.9 days, with October (71.7 mm), December (69.6 mm) and November (69.5 mm) the wettest months.
Many people with arthritis or osteoarthritis say their joints feel worse in cold, wet spells. We cannot promise that weather changes the disease itself, and nothing in medical guidance here says so. What is practical is that morning stiffness and a short walk to the car feel harder in a dark, damp winter. Sunshine is also limited: December averages only 55.3 hours, while May and July reach 191.5 hours each.
This matters for planning. After a procedure the joint may ache a little more for about a week, which is an expected reaction. Pain usually eases around one month, mobility and activity improve at about three months, and the full effect develops at about six months. Choosing a start date with these stages in mind lets you resume walking and exercise gradually in better conditions, though the doctor gives the load recommendations for your own case.
Summers can be hot as well: about 11 days a year reach 25 °C or above, and Watnall recorded 39.8 °C on 19 July 2022. If you have a skin inflammation over the joint, a fever, a cold or flu, the procedure is postponed, so it is sensible to tell the coordinator about any such symptoms.
Almost 62,000 students attend Nottingham's three universities, and the city hosts events such as the Robin Hood Marathon, the Nottingham Trophy tennis tournament and the Outlaw Triathlon. A busy sporting calendar means plenty of sprains, overuse and old injuries that come back years later.
The treatment programme lists several joints where this shows up. The ankle may stay painful and stiff after sprains and old injuries. The knee can suffer cartilage wear or meniscus trouble. The elbow aches after strain from sport or overuse. Recovery after injuries and surgery is also on the list of reasons people ask for a review.
High load on the joints, whether from sport or physical work, is one of the situations in which the treatment may be considered. Whether PRP alone, or PRP combined with SVF, is appropriate depends on the joint and the stage, and the doctor settles the joint, the method and the number of injections after checking your scans. If a runner or a cyclist wants to go back to training, ask for specific guidance on load and exercise in the first weeks.
According to Arthritis UK, over 10 million adults, young people and children in the UK live with arthritis. The NHS describes osteoarthritis as the most common type in the UK. Risk rises with age, is higher in women than in men, and is higher in people with obesity or a previous joint injury. A GP may suspect it in people aged 45 or older.
Body weight is a factor that is worth discussing frankly. The Health Survey for England 2022 reported that 29% of adults were living with obesity and 64% were overweight or living with obesity. Nottingham is in the East Midlands region. The same service text notes that how long a result lasts depends on the stage of the condition, body weight, activity and other factors, so no one can promise a fixed outcome.
It also helps to separate two conditions. Osteoarthritis is gradual wear of the cartilage, with aching pain on movement, crunching and stiffness after rest. Arthritis is inflammation, with pain at rest and at night, morning stiffness lasting more than 30 minutes, swelling, redness and warmth. The NHS notes that there is no cure for rheumatoid arthritis and that treatment is long-term medicine plus physiotherapy; our treatment is not a replacement for that care, and the doctor will tell you honestly what it can and cannot do.
The NHS may consider hip replacement when pain and stiffness have a big effect on life and other treatments have not worked, with osteoarthritis named as the leading cause. NHS England's statistics for the end of July 2026 show 7.3 million waiting pathways, around 6.2 million unique patients, and 111,379 people waiting more than 52 weeks. For someone in pain, a long wait raises an understandable question: is there anything to try in the meantime?
A free second opinion is one practical answer. You send your X-rays, MRI, CT or reports, and a doctor reviews them without charge and tells you whether the procedure could suit you and what else may be needed. For a joint that is already badly damaged, replacement may be the more realistic option, and the doctor says so plainly. At early stages of avascular necrosis of the hip (stages 1–2), SVF therapy may be considered to delay the need for replacement.
Replacement is major surgery with long rehabilitation, risks such as infection, and implants that may eventually need to be redone. That is why, with early or moderate changes, it often makes sense to try to preserve your own joint first. The consultation carries no obligation to book anything.
The first stage is online. Coordinators reply on WhatsApp and Telegram round the clock, and the free consultation covers a review of scans you already have. Gather your most recent X-ray, MRI or ultrasound images and any written reports, and note which joint hurts, when, and which painkillers you take.
England and Wales have 8 bank holidays in 2026, from Good Friday on 3 April to the Boxing Day substitute on 28 December. Messages can be sent on any of those days, so holidays need not delay a first review.
A procedure itself is done in one day: a blood sample for PRP, roughly 30 ml of adipose tissue under local anaesthetic if SVF is used, processing in a centrifuge, and then injection under ultrasound. There is no hospital stay, and the doctor stays in touch to follow how the joint responds. Costs depend on the joint, the stage and the method, and are stated after the consultation.
No. Weather is not a contraindication. What matters is your health on the day: skin inflammation over the joint, a fever, a cold or flu mean the procedure is postponed. Otherwise the timing is chosen with the doctor, bearing in mind that the joint may ache a little more for about a week.
The NHS describes osteoarthritis as the most common arthritis in the UK and offers hip replacement when other treatments have not worked. The programme here is a different option: an injection of your own blood and adipose tissue, which may suit earlier or moderate stages. The doctor reviews your scans first.
Yes. Send your X-ray, MRI, CT or reports to the coordinator on WhatsApp or Telegram. A doctor reviews them free of charge and says whether the procedure could suit you and what else may be needed. There is no obligation.
Yes, it is one of the factors named, together with the stage of the condition and activity. No one can promise a fixed result. The doctor discusses this with you at the consultation, based on your own case.
Knee, hip, shoulder, elbow, hand and wrist joints, and ankle can be treated. The doctor settles the joint, the method and the number of injections after checking your scans.
Yes. The consultation, the review of your scans and the discussion of a plan all take place online. Coordinators answer round the clock, and you can send images in advance.
Recent scans, written reports, a list of medicines, and a short description of where and when the joint hurts. Mention any fever, cold, flu or skin inflammation near the joint, as these cause a temporary delay.
Yes. Osteoarthritis is wear of the cartilage; arthritis is inflammation, often with pain at rest and at night. The approach differs, so the diagnosis comes first and the doctor assesses it from your scans.