
























Bariatric surgery6 min read
Gastric band vs sleeve and bypass: why banding is used much less today
Not long ago the adjustable gastric band was one of the most popular weight loss operations. Today it is performed far less often, while sleeve gastrectomy and gastric bypass have become the standard options. This guide explains how a band works, why it was once favoured, what problems appear over time and what people who already have a band can do.
The main points in 30 seconds
- A gastric band is an adjustable silicone ring that restricts how much food the stomach holds.
- Bands were popular because they were quick, adjustable and removable.
- Over the years many bands cause slippage, erosion, port problems or weight regain.
- Sleeve and bypass usually give more and longer-lasting weight loss than a band.
- Today bands make up only a small fraction of bariatric operations worldwide.
Key facts about the procedure
- Back to work2–4 weeks
- Stay in clinic1–5 days
- Final result18–24 months
- Price
$4,800from $3,600
How a gastric band works
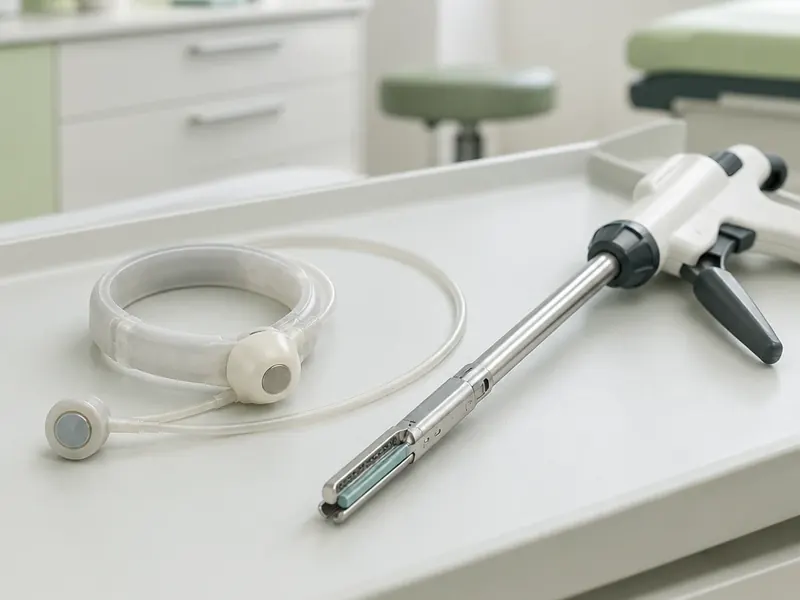
An adjustable gastric band is a silicone ring placed around the upper part of the stomach during keyhole (laparoscopic) surgery. It creates a small pouch above the band, so a person feels full after a small amount of food. Nothing is cut or stapled and the digestive tract is not rerouted.
The inner surface of the band contains an inflatable balloon connected by a thin tube to a port placed under the skin of the abdomen. By injecting or removing saline through the port, the doctor can tighten or loosen the band. Several adjustments are usually needed in the first year to find the right level of restriction.
A band works purely by restriction. It does not change the gut hormones that control hunger in the way sleeve gastrectomy and gastric bypass do, so the result depends heavily on eating habits and regular follow-up.
Why bands were popular
In the 1990s and 2000s the band seemed an attractive solution for many patients and surgeons:
- the operation is relatively quick and the stomach is not divided;
- the hospital stay is short and early recovery is usually easy;
- the band can be adjusted as weight changes;
- it is technically removable, which reassured people worried about permanent changes.
These advantages are real, but long-term follow-up studies over the next decades showed that the band often did not deliver the lasting results people hoped for.
Side effects and long-term complications
Early complications after banding are relatively uncommon, but problems tend to build up over the years. Commonly reported issues include:
- Vomiting and food intolerance, especially with solid foods, if the band is too tight or food is not chewed well.
- Band slippage, where the band shifts and the pouch enlarges, causing pain, vomiting or blockage.
- Erosion, when the band gradually wears into the stomach wall.
- Port and tube problems, such as infection, leaks, disconnection or the port turning over.
- Reflux and widening of the oesophagus above a tight band.
- Weight regain, often because people switch to soft, high-calorie foods that pass the band easily.
A significant share of patients eventually need another operation to reposition or remove the band, which is one of the main reasons its use has fallen.
Results compared with sleeve and bypass
Weight loss varies widely from person to person, but published data generally show that bands produce less weight loss and more reoperations than stapled procedures.
How it works
- Adjustable gastric band
- Restriction with an adjustable ring
- Sleeve gastrectomy
- Most of the stomach is removed, hunger hormones decrease
- Gastric bypass
- Small pouch connected to the small intestine
Typical excess weight loss
- Adjustable gastric band
- Often lower and very variable
- Sleeve gastrectomy
- About 60–70% on average
- Gastric bypass
- About 75–85% on average
Main drawbacks
- Adjustable gastric band
- Slippage, erosion, port problems, regain, frequent reoperations
- Sleeve gastrectomy
- Reflux in some patients, possible regain without diet changes
- Gastric bypass
- Lifelong vitamin and mineral supplements
Sleeve gastrectomy and bypass also tend to have a stronger effect on related conditions such as type 2 diabetes and high blood pressure, because they change hormonal signals as well as the size of the stomach.

Why banding is used less today
International data show that gastric bands now make up only a small fraction of bariatric operations, while sleeve gastrectomy and bypass account for the great majority. The main reasons are:
- less and less durable weight loss compared with stapled procedures;
- a high rate of complications and repeat surgery over the long term;
- the need for frequent adjustments and close follow-up;
- the weaker effect on diabetes and other obesity-related conditions;
- laparoscopic sleeve and bypass have become safer and more predictable.
A band may still be discussed for selected patients, but for most people with severe obesity surgeons now recommend other options.
Options if you have a band
If your band works well, you have no symptoms and your weight is stable, it can stay in place with regular follow-up. Never try to adjust the band or the port yourself.
See a specialist promptly if you have repeated vomiting, difficulty swallowing, heartburn, pain around the port or weight regain. Depending on the findings, options include loosening the band, removing it, or removing it and converting to a sleeve gastrectomy or gastric bypass. Conversion may be done in one operation or in two stages; the surgeon decides based on the condition of the stomach and your general health.
For people considering bariatric surgery for the first time, the question today is usually not whether to choose a band, but which stapled operation suits their weight, related conditions and lifestyle. At a consultation about bariatric surgery at City Medical Centre, the surgeon explains the options that fit your situation.
Modern bariatric options at City Medical Centre
City Medical Centre works with international patients and performs laparoscopic bariatric operations: sleeve gastrectomy, Roux-en-Y gastric bypass, mini gastric bypass (one anastomosis) and SADI-S, which can also serve as a second stage after an ineffective sleeve. Whether gastric band placement, band removal or conversion of a band to a sleeve or bypass is performed at the clinic and whether it suits you is clarified at the free consultation. Information about bands in this article is general.
The first consultation is free and can be held online: send your height, weight and medical history via Telegram. The cost is named after the assessment and fixed in the contract, a personal coordinator stays with you from your first message to the end of recovery, and specialists follow your progress during the first year. Learn more on the bariatric surgery page.
How recovery usually goes
- First hoursYou may sit up, stand and drink fluids
- 1–5 daysObservation at the clinic, depending on the extent of surgery
- 2–4 weeksReturn to office work; physical work after about 1.5 months
- 1–2 monthsStaged diet from liquids to solids to let the stomach adapt
- Every monthOn average 10% of excess weight lost per month
- 1.5–2 yearsFinal result, stable eating habits prevent the weight from returning
Sources
Frequently asked questions
Is a gastric band still a good option?
For most people with severe obesity it is no longer the first choice. Bands usually lead to less weight loss than sleeve gastrectomy or bypass, and many patients need further surgery over the years. A band may still be discussed in selected cases, but surgeons now recommend stapled procedures far more often.
Why do gastric bands fail?
Common reasons are complications such as slippage, erosion or port problems, and weight regain when people switch to soft, high-calorie foods that pass the band easily. A band also does not change hunger hormones, so the result depends heavily on eating habits and regular adjustments.
Can a band be converted to a sleeve or bypass?
Yes, in many cases. The band is removed and a sleeve gastrectomy or gastric bypass is performed, either in the same operation or in two stages. The surgeon decides after examining the stomach, often with gastroscopy, and assessing your general health and weight history.
How much weight can you lose with a band?
Results vary widely. Some people lose a meaningful amount of excess weight, but on average the loss is lower and less stable than after sleeve gastrectomy, where about 60–70% of excess weight is typically lost, or bypass, with about 75–85%. Long-term follow-up is essential.
What are the long-term band complications?
Reported long-term problems include band slippage, erosion into the stomach wall, port infection or leaks, reflux, widening of the oesophagus, persistent vomiting and weight regain. Any of these may require the band to be adjusted, repositioned or removed, so symptoms should be checked by a specialist.
Have a question about your case? Get a free consultation
Message a coordinator on Telegram: we reply right in the chat, and you can send photos and questions there too.
- The first consultation is free, online consultations are available
- The doctor names the cost after the assessment, and it is fixed in the contract
- A personal coordinator guides you from the first message to recovery
Message our coordinator on Telegram
We reply right in the chat — you can send photos
Message us on TelegramBy sending a message, you agree to the privacy policy
Read also
 Bariatric surgery
Roux-en-Y gastric bypass explained: how the operation works and who it suits
How Roux-en-Y gastric bypass works, who it suits best, expected weight loss and diabetes effects, dumping syndrome, lifelong vitamins and recovery.
 Bariatric surgery
Sleeve gastrectomy explained: how the operation works and who it suits
Gastric sleeve explained: how the operation is done, who it suits, expected weight loss, sleeve vs bypass, risks, recovery and conversion options later.
 Bariatric surgery
Diet after gastric sleeve surgery: stages from liquids to solid food
Diet after gastric sleeve surgery: liquid, purée, soft and regular food stages, protein and water, portions, foods to avoid, vitamins and long-term habits.